What the Anion Gap Shows
The anion gap is a calculated value that helps medical professionals interpret an electrolyte panel by assessing the balance between measured plasma ions. It is not directly reported on most lab results, but it can be derived from the numbers that are already present in routine testing. Because it shows the difference between major measured cations and anions, it offers an important window into acid-base balance.
An high or abnormally low result can serve as a diagnostic clue when reviewing lab results. In practice, the anion gap is most helpful for recognizing an acid-base disorder, especially metabolic acidosis. It also supports broader clinical interpretation of electrolyte values by pointing toward hidden acid accumulation, unmeasured ions, or a shift in protein-related charge balance.
An anion gap calculator streamlines this process by turning routine measurements into a quick gap analysis. That can be especially useful when a clinician is reviewing an electrolyte imbalance or trying to connect a chemistry panel with the patient’s symptoms, history, and possible toxin exposure.
Anion Gap Calculator Method and Parameters
The core formula for calculation uses the most common blood electrolytes: sodium, chloride, and bicarbonate. In many cases, potassium may also be included, even though the simplified formula often excludes it.
A typical version is:
Anion gap = sodium − (chloride + bicarbonate)
When potassium is included, the formula becomes:
Anion gap = sodium + potassium − (chloride + bicarbonate)
The exact version used can vary depending on the lab and the reference interval used for interpretation. That is why an anion gap calculator should always be paired with the lab’s own reporting conventions and the patient’s overall condition.
These values matter because they reflect the major measured ions in the sample. Serum sodium represents the dominant measured cation, while serum chloride and serum bicarbonate are major measured anions. The resulting number estimates the amount of unmeasured anions in the blood, which can signal acid accumulation or a shift in protein binding.
How to Work Out Anion Gap Stepwise
To calculate the anion gap, use the serum electrolytes from a recent chemistry panel. Typically, these results come from a basic metabolic panel or a comprehensive metabolic panel. Then use the formula based on the numbers reported for sodium, chloride, and bicarbonate.
Step by step, the process looks like this:
- Note the reported sodium value. Identify the chloride value. Identify the bicarbonate value. Add chloride and bicarbonate together. Subtract that total from sodium.
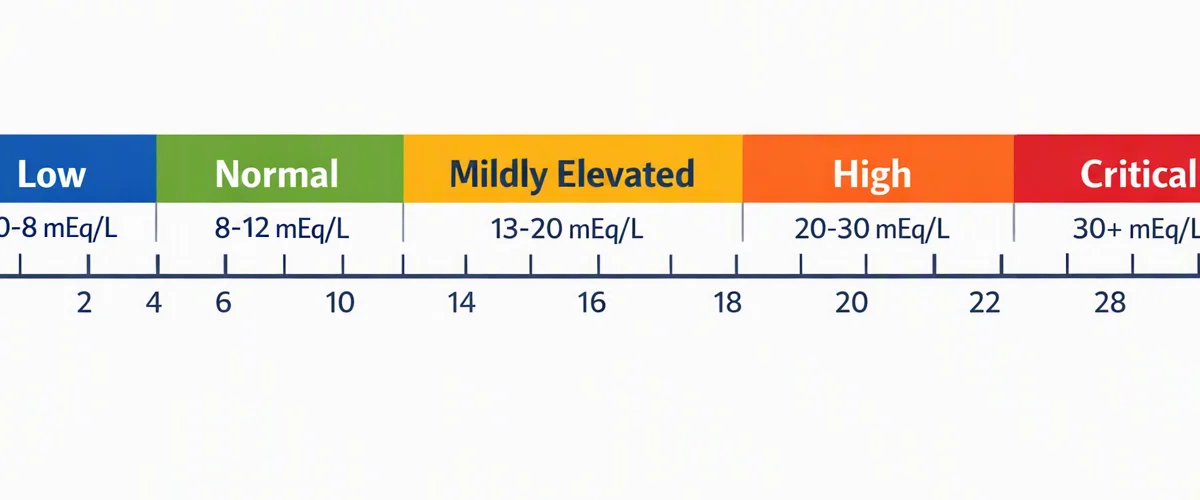
As an example, if sodium is 140, chloride is 102, and bicarbonate is 24, the calculation is 140 − (102 + 24) = 14. This result can then be compared against the local normal range.
When potassium is part of the formula used by a specific lab or tool, factor it in the sodium side of the equation. Since different panels may report values in slightly different units or formats, unit conversion should always be checked before interpreting the result. A small mismatch in units can create a misleading answer even when the calculation formula is applied correctly.
In clinical use, the calculation is quick, but interpretation is more vital than the number alone. The anion gap should be viewed in light with the full set of electrolyte values, the patient’s symptoms, and any sign of an acid-base disorder.
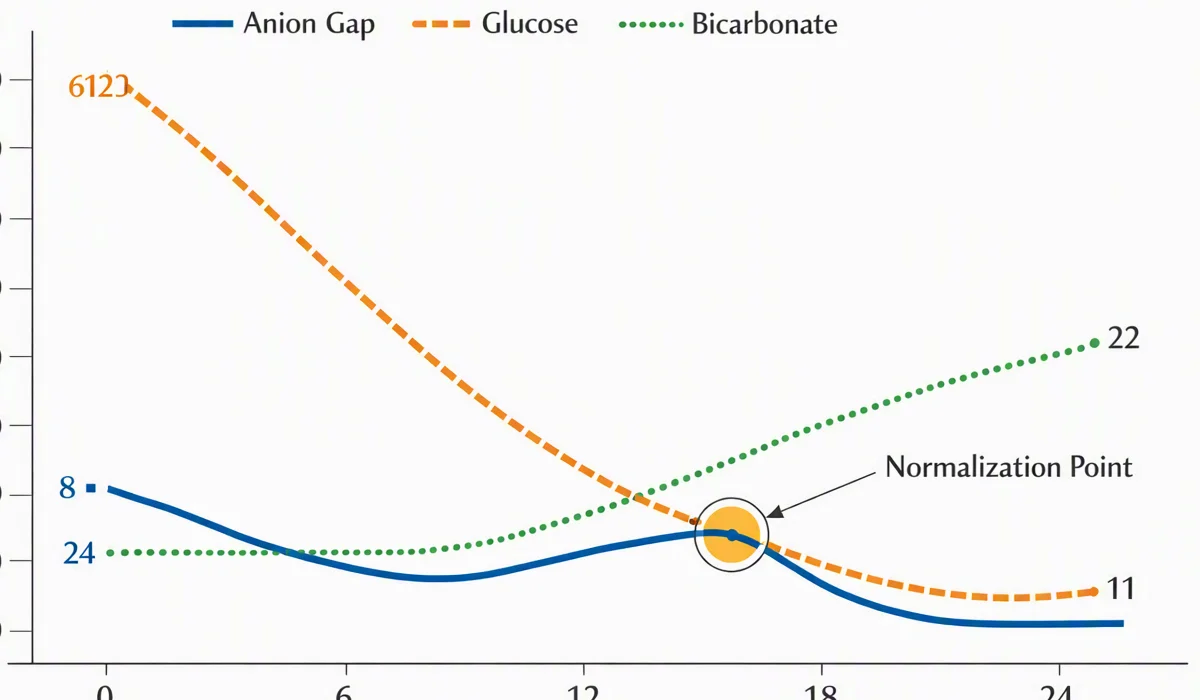
Normal Anion Gap versus Increased Anion Gap
A typical anion gap usually means the difference between measured cations and anions falls within the expected reference range. This does not always mean the patient is healthy, but it implies there is no obvious increase in unmeasured acids based on the panel alone.
A high anion gap often points to a metabolic acid buildup. In this setting, extra acids accumulate in the body, bicarbonate is consumed as it buffers those acids, and the gap rises because the unmeasured anions increase. This is why the anion gap is such a useful clinical clue when analyzing lab results.
In lab interpretation, the distinction between normal and high values matters because it guides the next step in evaluation. A high result may prompt review for acid overload, kidney dysfunction, or toxin ingestion. A normal result may shift attention toward bicarbonate loss or chloride gain. Either pattern can reflect a significant metabolic derangement.
Frequent Reasons of a High Anion Gap
A high result is commonly linked to a number of important conditions. One of the best-known causes is lactic acidosis, in which lactate accumulates when tissues are not receiving enough blood flow or when metabolism is impaired. Another major cause is ketoacidosis, where ketone bodies rise during insulin deficiency, starvation, or severe metabolic stress.
Renal failure can also raise the anion gap because impaired kidneys cannot clear acids effectively. As renal function declines, acid retention leads to acid accumulation and a declining metabolic picture. This is one reason the anion gap is often reviewed alongside kidney-related chemistry findings.
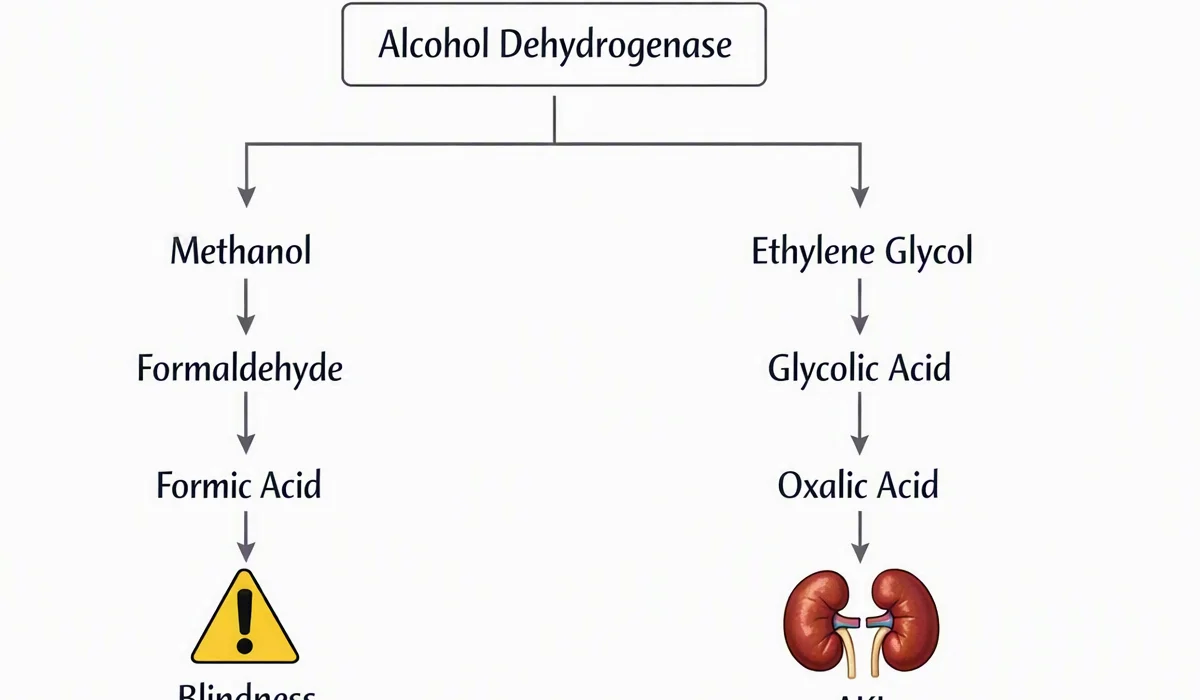
Toxic alcohols are another critical cause. Ingestion of substances such as methanol or ethylene glycol can result in severe acid-base changes and a dangerously high gap. In this setting, the anion gap becomes a major sign of possible toxin exposure and may demand urgent evaluation.
Other high-gap conditions exist as well, but these four are among the most clinically important conditions. A thoughtful review of the history, symptoms, and lab results helps determine whether the elevated number is due to poor perfusion, ketone production, renal impairment, or a toxic ingestion.
Frequent Causes of a Normal Anion Gap
A normal anion gap does not rule out a significant problem. It may instead suggest a distinct type of acid-base disturbance, especially one driven by loss of bicarbonate rather than acid accumulation. One common cause is loose stools, which can lead to considerable loss of bicarbonate from the digestive tract.
Renal tubular acidosis is another important cause. In this condition, the kidneys cannot process acid and bicarbonate correctly, leading to a pattern that often shows a normal anion gap despite continued metabolic problems. The issue may be hard to notice, but the chemistry pattern is a clear clue.
Loss of bicarbonate from any source can produce this pattern, and that makes bicarbonate depletion key to the interpretation. To maintain electrical neutrality, the body often holds onto chloride, which leads to hyperchloremia. The result is a normal gap with a changed chloride-bicarbonate relationship.
This pattern is sometimes described as hyperchloremic metabolic acidosis. Even though the anion gap remains in range, the patient may still have a significant acid-base problem that deserves attention.
Modified Anion Gap and Albumin
Albumin acts as one of the https://anion-gap-calculation.com/special-populations/elderly.html most important unmeasured anions in blood, so its level can significantly affect the anion gap. When albumin is low, the gap may seem deceptively normal or only mildly elevated even if a major acid-base problem is present. This is why hypoalbuminemia must always be considered during interpretation.
The corrected anion gap adjusts for low albumin and gives a more accurate picture of the patient’s true acid-base state. This process is often called albumin correction. Without it, clinicians may misjudge the severity of the metabolic disturbance.
The reason is related to protein binding. Albumin holds negative charge in the bloodstream, so when albumin drops, the measured gap can decrease even if other acids are present. Correcting for albumin helps uncover hidden abnormalities that might otherwise be missed.
For example, a patient with a ostensibly normal gap and marked hypoalbuminemia may actually have a clinically significant high-gap process once the correction is applied. That is why albumin should be reviewed whenever the result does not match the clinical picture.
When to Apply an Anion Gap Calculator
An anion gap calculator is particularly valuable whenever a clinician is assessing an electrolyte panel for indicators of an acid-base imbalance. It can be applied to a basic metabolic panel or a comprehensive metabolic panel, both of which usually include the values needed for the formula.
It is especially helpful as a form of clinical decision support when the patient has signs that could reflect metabolic instability, such as dehydration, altered mental status, unexplained illness, or suspected poisoning. It can also aid structuring the evaluation of low bicarbonate or other lab abnormalities into a better defined diagnostic pathway.
Because the calculator provides a fast summary of key serum electrolytes, it can support bedside reasoning and inform follow-up testing. Still, it should never replace clinical context. A numeric result is most informative when interpreted with the full picture of lab findings, history, and physical exam.
Limitations and Frequent Calculation Errors
Even though the formula is straightforward, several factors can affect accuracy. Lab variability is one issue, since different analyzers and reporting methods can yield slightly different values. That means two panels from different labs may not line up exactly, even when the patient’s condition has not changed.
The chosen reference range also matters. What counts as normal in one setting may differ in another, especially if the lab uses a different calculation method or includes potassium. This makes it important to interpret the result using the correct local standard rather than relying on a single universal cutoff.
Measurement error can occur if a sample is mishandled, diluted, or otherwise compromised. In some cases, a lab artifact may create a misleading result that does not reflect the patient’s true physiology. Repeating the test or comparing it with the broader clinical picture can help identify these issues.
One practical pitfall is assuming that a “normal” number always means there is no problem. Another is forgetting to account for albumin, which can hide a substantial gap. Careful review of the full panel and awareness of potential error sources raise the quality of interpretation.
Frequently Asked Questions on Anion Gap Interpretation
What does an anion gap calculator used for?
An anion gap calculator is designed to turn an electrolyte panel into a helpful estimate of unmeasured ions in the blood. It supports clinical interpretation of lab results, especially when evaluating metabolic acidosis, acid accumulation, or an unexpected electrolyte imbalance. It is a handy tool for reviewing sodium, chloride, and bicarbonate together.
How do you determine anion gap from an electrolyte panel?
Use the calculation formula: sodium minus the sum of chloride and bicarbonate. In some settings, potassium is included as well. The values usually come from serum electrolytes on a basic metabolic panel or comprehensive metabolic panel. After calculating, compare the result with the lab’s normal range or reference interval.
What can a high anion gap mean?
A high anion gap usually suggests metabolic acidosis caused by added acids or unmeasured anions. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. The result is a helpful sign that points toward acid accumulation and helps narrow the differential diagnosis.
In what way does low albumin affect the anion gap?
Low albumin can lower the measured gap because albumin contributes negative charge in blood. With hypoalbuminemia, the apparent result may underestimate the true disorder. A corrected anion gap uses albumin correction to better reflect the actual acid-base balance and avoid missing important abnormalities.
Could a typical anion gap also suggest a major condition?
Yes. A typical anion gap can also occur with serious conditions such as diarrhea, renal tubular acidosis, or various causes of bicarbonate loss. Hyperchloremia may also be seen. So a normal result does not automatically eliminate an acid-base disorder; it only points to a varied pattern of disturbance.