How the Anion Gap Reflects
The anion gap is a formula used to analyze serum electrolytes and detect hidden acids in the blood. An anion gap calculator typically uses sodium, chloride, and bicarbonate to approximate the difference between measured positively charged and negatively charged ions. That difference can point to a metabolic derangement such as acid buildup.
At its core, the anion gap formula captures the balance of major ions on a standard electrolyte panel. When chloride and bicarbonate vary in relation to sodium, the calculated gap varies. A higher-than-expected result suggests that unmeasured acids may be present in the bloodstream.
Because the anion gap is derived from routine blood chemistry, it is often used in the initial diagnostic workup of an acidotic state. It does not diagnose a disease by itself, but it helps narrow the underlying cause. In that way, it is a practical tool for clinical interpretation of acid-base disorders.
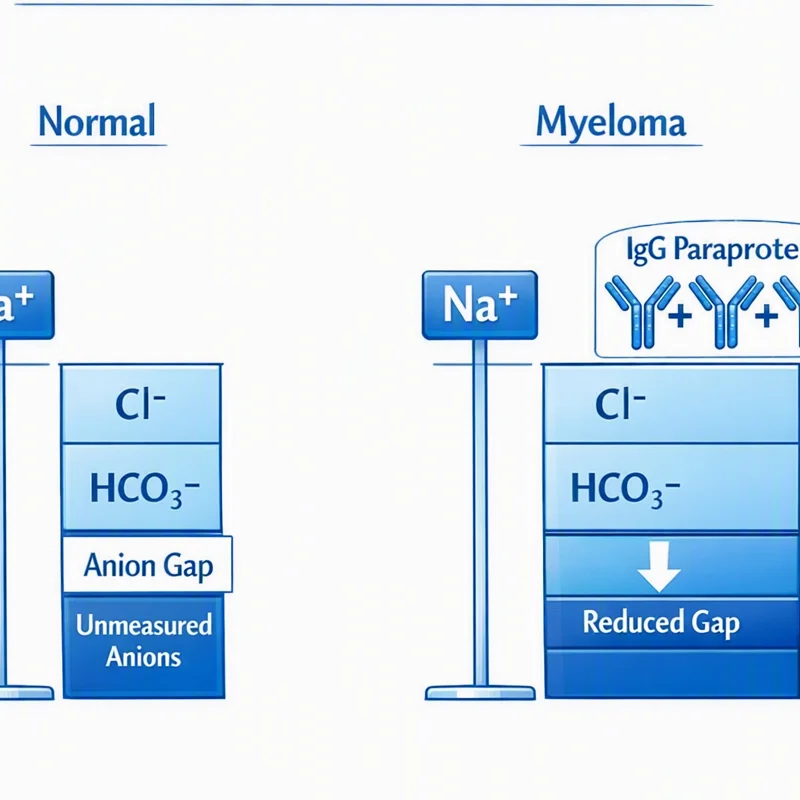
Normal values vary by laboratory, so the normal range depends on the assay and method used. Since albumin carries a negative charge, a low albumin level can make the measured gap appear smaller than it truly is. That is why clinicians often consider a corrected anion gap rather than relying on the raw number alone.
How Oxygen deficiency Influences acid-base status
Hypoxia means insufficient oxygen at the tissue level, and tissue hypoxia can quickly disrupt acid-base balance. When cells do not receive enough oxygen, they cannot rely on normal oxygen-based energy production. Instead, they shift toward anaerobic metabolism, especially anaerobic glycolysis, which generates more lactate.
This shift is a form of oxygen deprivation response. The body tries to preserve energy production, but the tradeoff is acid accumulation. As lactate production rises, hydrogen ion burden also increases, pushing the body toward an acidotic pattern. That is why prolonged hypoxia can anion gap be linked to lactic acidosis.
The link between hypoxia and acid-base changes is not just about low oxygen in the blood. It often reflects cellular hypoperfusion, where oxygen delivery is impaired because blood flow is inadequate. In that setting, tissues become starved for oxygen even if the lungs are working to some degree. The result is a metabolic shift that can worsen a metabolic acidosis.
The body may mount a compensatory response, such as faster breathing, to reduce carbon dioxide and partially offset the acid load. Still, if the underlying problem continues, the metabolic disturbance can deepen. That is why hypoxia deserves attention whenever a patient has unexpected changes in blood gases or electrolytes.
Can Low oxygen Increase the Anion Gap?
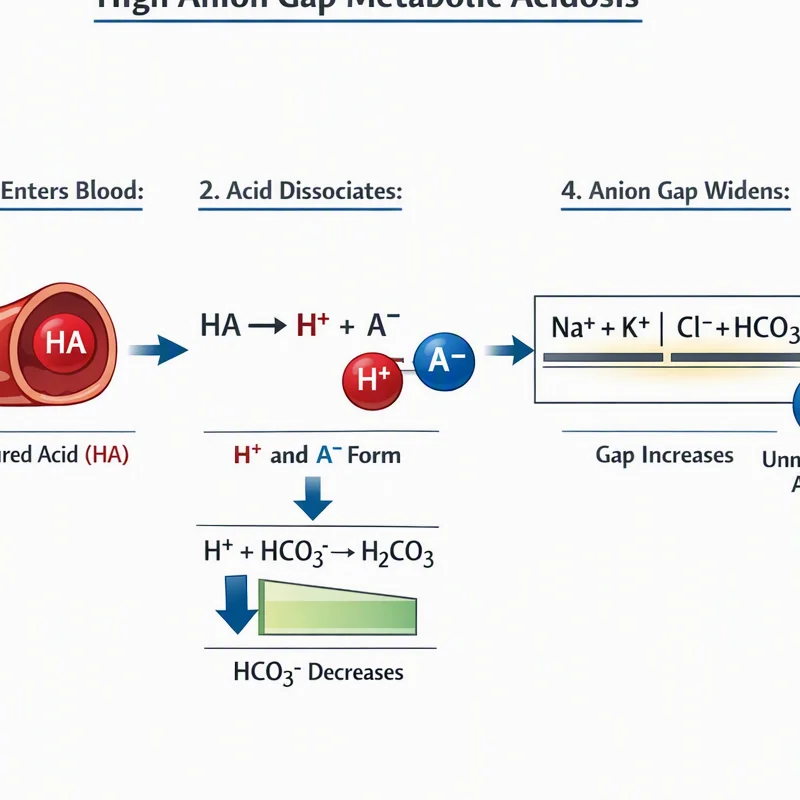
Absolutely. Low oxygen can raise the anion gap when it produces high anion gap metabolic acidosis, most commonly through lactic acidosis. When oxygen delivery is reduced, cells switch to anaerobic energy pathways, and lactate builds up. Because lactate is an unmeasured anion, it elevates the gap calculated from the standard anion gap calculation.
This is why the answer is not simply “hypoxia raises the anion gap” in every case. It is more precise to say that oxygen deprivation can lead to elevated lactate, and elevated lactate can produce a high gap. The laboratory pattern depends on severity, duration, and the presence of other illnesses. A patient with mild low oxygen may not show major acid-base changes, while a patient with profound tissue hypoxia may develop clear metabolic acidosis.
In clinical practice, a rising anion gap often suggests that the body is accumulating acids faster than it can clear them. With hypoxia-related disease, the main acid is usually lactate. That makes lactate measurement important when the anion gap calculator result seems abnormal and the patient has signs of poor perfusion or respiratory compromise.
A useful way to think about it: hypoxia does not directly “create” the gap, but it can trigger acid production that increases the gap.
So the relationship is indirect but important. Hypoxia leads to metabolic stress, metabolic stress leads to anaerobic metabolism, and anaerobic metabolism can lead to lactate accumulation. That chain is the physiology behind many cases of elevated gap acidosis in critical illness.
When Hypoxia Fails to Raise the Anion Gap
Not all patient with hypoxia shows an elevated gap. Some people may have changes in breathing without a large acid load. For example, respiratory alkalosis can occur early in hypoxemia because the person hyperventilates and lowers carbon dioxide. In that situation, the anion gap may continue to be normal even though oxygen levels are low.
Likewise, respiratory acidosis may happen when ventilation is poor, but that problem primarily raises carbon dioxide rather than producing a major load of unmeasured acids. The anion gap may stay within the expected normal range if there is no substantial metabolic component. These conditions show why blood gas results and electrolyte data must be interpreted together.
A patient may also have hypoxia with only slight or transient metabolic acidosis. If the episode is transient, lactate may not rise enough to change the lab picture significantly. In other cases, the body removes lactate quickly once oxygen delivery improves. The result is a typical or near-normal gap despite a clear hypoxic event.
This difference matters because the anion gap is a marker of acid load, not oxygen level itself. You can have low oxygen without major acid accumulation. For that reason, an abnormal gap should prompt assessment for the actual metabolic cause, while a normal gap does not rule out significant hypoxia.
Additional Frequent Reasons of a Elevated Anion Gap
Hypoxia is only an possible reason for raised anion gap results. Further frequent causes include ketoacidosis, renal failure, uremia, and toxic alcohols. Each of these conditions produces unmeasured acids that increase the calculated gap.
Ketoacidosis happens when the body breaks down fat and produces ketones faster than they can be used or eliminated. That may be found in diabetes, starvation, or alcohol-related illness. The result is a increased-gap metabolic acidosis that can resemble lactic acidosis on first glance.
Renal failure causes impaired acid excretion, allowing organic acids and sulfate compounds to accumulate. In advanced kidney dysfunction, uremia becomes a key contributor to elevated gap acidosis. The kidneys cannot clear acids effectively, so the blood becomes progressively more acidotic.
Toxic alcohols such as methanol and ethylene glycol also cause dangerous acid-base disturbances. These substances are metabolized into acids that increase the anion gap. Because these cases can be life-threatening, a high gap should always be interpreted in the context of history, exposure risk, and the broader clinical picture.
How to Read an Anion Gap Calculator Result
If you are using an anion gap calculator, first review the input values for sodium, chloride, and bicarbonate. The output gives a snapshot of the current electrolyte relationship, but the number alone is not enough. How it is interpreted depends on albumin, the patient’s condition, and whether there is a mixed acid-base disorder.
When albumin is low, the measured gap may underestimate the true degree of acid accumulation. That is why clinicians may apply a corrected anion gap. This adjustment helps avoid missing a significant metabolic disturbance in patients with malnutrition, liver anion gap Anion-Gap-Calculation.com disease, or prolonged hospitalization. In other words, albumin can mask clinically meaningful changes.
It is also essential to check bicarbonate. A low bicarbonate level supports the presence of metabolic acidosis, especially if the gap is elevated. However, bicarbonate alone does not reveal the cause. An elevated gap plus low bicarbonate suggests a process such as lactic acidosis, ketoacidosis, renal failure, or toxin exposure.
An arterial blood gas provides another layer of information. It helps determine pH, carbon dioxide, and compensatory patterns. When combined with the anion gap, it improves clinical interpretation and helps distinguish whether the issue is metabolic, respiratory, or mixed. This combined approach is more reliable than any single lab result.
Clinical Indicators That Suggest Acidosis Related to Hypoxia
Hypoxia-driven acidosis is often suspected when low oxygen saturation occurs alongside elevated blood lactate. A increasing lactate level indicates that tissues are shifting toward anaerobic metabolism because oxygen delivery is inadequate. This is one of the clearest clues that hypoxia is driving the metabolic picture.
Conditions such as sepsis and shock frequently cause this pattern. In sepsis, poor circulation and cellular dysfunction can cause tissue hypoperfusion even before blood pressure declines significantly. In shock, oxygen delivery is markedly impaired, which can drive notable lactate accumulation and a high anion gap.
Other signs may include rapid breathing, cool extremities, weak pulses, low urine output, or deteriorating mental status. These findings point toward a systemic metabolic derangement rather than a simple isolated lab abnormality. The lab pattern becomes especially important when it aligns with the bedside picture of poor perfusion.
When these clues are present, the anion gap is best viewed as a marker of clinical severity and metabolic stress. It does not replace clinical evaluation. Instead, it supports it by showing whether acid buildup has already become substantial enough to alter the blood chemistry.
When You Should Seek Urgent Medical Evaluation
Prompt medical care is needed if hypoxia or a high anion gap occurs with confusion, shortness of breath, chest pain, or altered mental status. These symptoms can signal marked oxygen deprivation, a significant acid-base disruption, or another critical medical issue. A delay in treatment can allow tissue injury to worsen.
A high anion gap plus breathing distress or poor circulation should be taken seriously. It may reflect severe lactic acidosis, sepsis, shock, or toxin exposure. In these situations, the right response is rapid medical assessment, oxygen support if needed, and a full diagnostic workup.
If the person is hard to wake, has labored breathing, or appears confused, emergency evaluation is especially important. These features may indicate an acidotic state with inadequate oxygen delivery. Timely treatment can improve oxygenation and acid-base balance.
Questions About Hypoxia and the Anion Gap
Can low oxygen result in a high anion gap?
Yes. Low oxygen can cause a high anion gap if it leads to tissue hypoxia and lactic acidosis. The key mechanism is anaerobic metabolism, which increases lactate and creates a high anion gap metabolic acidosis. This does not happen in every case of low oxygen, but it is a classic finding in severe illness.
Why does hypoxia lead to lactic acidosis?
When oxygen delivery is inadequate, cells rely more on anaerobic glycolysis to make energy. That pathway produces more lactate than normal aerobic metabolism. As lactate increases, acid accumulation follows, producing lactic acidosis and potentially a higher anion gap.
Will every patient with hypoxia develop an elevated anion gap?
No. A patient can have hypoxia without a high anion gap. Mild or short-lived oxygen deprivation may not cause enough lactate buildup to change the gap. Some patients may instead show respiratory alkalosis or a mixed pattern depending on the cause and duration of illness.
In what way does albumin alter the anion gap calculation process?
Albumin is a key unmeasured anion, so reduced albumin can cause the measured gap look artificially low. For this reason a corrected anion gap may be calculated. Correcting for albumin helps reveal the true extent of acid-base abnormality and improves clinical interpretation.
What additional conditions can increase the anion gap besides hypoxia?
Other important causes include ketoacidosis, renal failure, uremia, and toxic alcohols. These disorders also produce unmeasured acids, leading to metabolic acidosis. An anion gap calculator helps detect the pattern, but the underlying cause still requires targeted evaluation.